
3. Accidents, Injuries & Chiropractic
Chiropractic care may assist with the musculoskeletal effects of car accidents, slip and fall injuries at home or work. Dr Jason Barritt, Canberra chiropractor, offers gentle, thorough initial evaluations.
Accidents and Injuries Come in Many Forms
When it comes to the kinds of injuries that affect the spine and musculoskeletal system, car accidents are just one part of the picture. Falls at home, low-speed collisions and sporting mishaps can all produce the same underlying damage. Understanding this can be an important first step towards better health and helping you to be more mobile in your senior years.

An everyday slip hazard can lead to a fall and musculoskeletal injury, with long term consequences even when the incident initially seems minor. Image credit: Alexas Fotos/Pexels.com
When most people think about accident injuries, they think about car accidents. But in Australia, one of the most common causes of serious injury is much closer to home - literally. According to the Australian Institute of Health and Welfare, in 2022-23 there were 238,055 hospitalisations due to falls across Australia, accounting for 43.4% of all injury-related hospital admissions. Critically, nearly half of all fall-related hospitalisations occur in the home - not at work, not on a sports field, but in the very place we feel safest. A trip on a step, a slip on a wet floor, a stumble getting out of the bath: these everyday moments can result in the same kinds of spinal and musculoskeletal injuries as a car accident.

A low-speed rear-end collision can appear minor while still exposing occupants to sudden movement of the neck and spine leading to serious injury. Image credit: Nikita Nikitin/Pexels.com
Australians are also familiar with the humble bingle - a low-speed collision that leaves both cars looking largely unscathed. What is less well understood is that the absence of visible vehicle damage does not by itself establish whether an occupant has been injured. There is a biomechanical reason for this that is worth understanding. At lower collision speeds, relatively little visible vehicle deformation may occur, but occupants can still be exposed to rapid acceleration and movement of the cervical spine. A clinical review reports that up to 42% of people are left with chronic symptoms following whiplash injury.1
What makes this especially important to know is that symptoms may not appear immediately. It is common for people to feel shaken but physically fine immediately after a bingle, only for neck pain, headaches or restricted movement to develop in the days, weeks - or even months - that follow. The same applies to falls around the home, a skiing injury on the Kosciuszko slopes, or any other seemingly minor traumatic event. Following an injury, changes in movement, muscle tension and joint function may persist over time. Previous joint injury has also been associated with an increased risk of later degenerative joint changes, although the pathway and contributing factors can vary considerably between individuals.
A study published in the journal Injury found that patients with a previous whiplash injury underwent cervical disc surgery at twice the rate of the general orthopaedic population, and at a significantly younger age - providing strong evidence that whiplash injury, even from a seemingly minor collision, can set the stage for premature degenerative disc disease.2
What Happens Inside the Body After Injury?
Many injuries that initially seem minor can set off a chain of events inside the body that, if left unaddressed, may develop into more significant long-term problems. Understanding this process helps explain why early assessment is often worthwhile.
It is also worth noting that whiplash-type injuries are not limited to car accidents. A sporting collision, being bumped from behind unexpectedly, or striking your head on a low ceiling or cupboard can all produce the same mechanism of injury: a rapid, unexpected movement that stretches and strains the ligaments supporting the spinal joints. When ligaments are stretched beyond their normal range, they can lose their ability to properly guide and limit movement between the bones they connect. The body responds to this instability with protective muscle guarding - a kind of involuntary splinting - along with localised inflammation and pain.
If the underlying joint dysfunction is not addressed, this process can become self-perpetuating. Orthopaedic researchers Kirkaldy-Willis and Farfan described this as a degenerative cascade, defined in their research as follows:
“Degeneration starts in one joint and eventually involves all three joints of the three-joint complex at an intervertebral level.”3”
The degenerative process progresses through stages of dysfunction, instability and ultimately arthrosis - also known as degenerative joint disease. In one study, patients with a history of whiplash were represented among people undergoing cervical disc surgery at twice the rate found in a general orthopaedic outpatient comparison group, and underwent surgery at a significantly younger age.2
Restoring proper motion to affected joints through chiropractic care is one approach that may help address this process. The chiropractic literature provides direct support for this. A systematic review published in Chiropractic & Manual Therapies - a peer-reviewed chiropractic journal - found that:
““Based on the studies reviewed herein, SMT sometimes seems to have a small effect on ROM, at least in the cervical spine.”4”
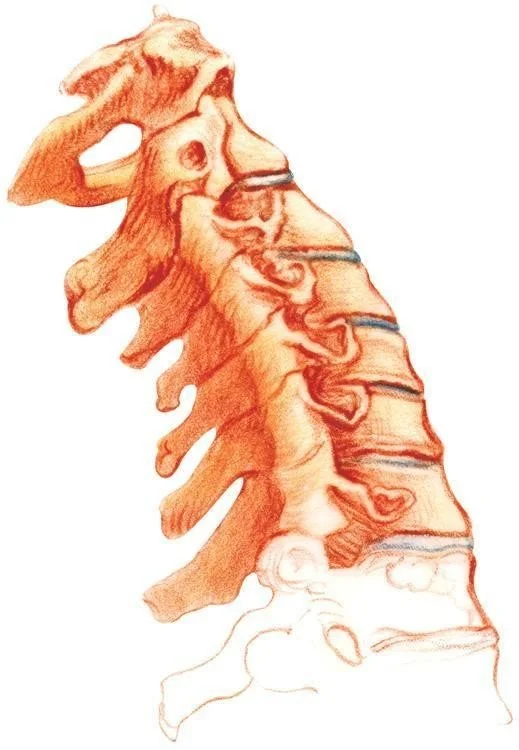
Anatomical illustration of the cervical spine,
the region most commonly affected in whiplash-type injuries.
Image credit: US NIH/NIAMS via Wikimedia Commons (public domain).
The chiropractic literature also sheds light on why this effect occurs. Research published in the Journal of Contemporary Chiropractic describes how spinal adjustment:
““Can cause changes to the surrounding soft tissue structures, remodel the state and viscosity of the facet joint’s synovial fluid, briefly alter the spinal joint mechanics, and elicit physiological changes modulated through the nervous system, like muscle tonicity, pain modulation, sensory changes and improved feedback abilities.”5”
A randomised trial summarising American Physical Therapy Association guidance states that:
““There is strong evidence to show that vertebral mobilisation and manipulation procedures can be used to improve spinal and hip mobility and reduce pain and incapacity”6”
- in patients with low back pain. Please note: as with all healthcare, individual results vary.
How Chiropractic Care May Help After Injury
Understanding how the body responds to trauma - and why injuries sometimes worsen without treatment - helps explain what chiropractic care aims to do.
Sometimes our world can be a dangerous place; many of us have experienced a traumatic brush (or collision) with reality. Accidents may be unavoidable, but much of the resultant pain and suffering may, in many cases, be safely and gently managed with chiropractic care. Within the cited chiropractic model, some people who have experienced trauma may also present with spinal dysfunction and altered sensory input from the affected area. Haavik and colleagues describe vertebral subluxation as a proposed model involving altered afferent input that may contribute to maladaptive changes in central neural processing and dysfunction.7 I have been studying and practicing chiropractic since 1990 and have taken many seminars in the area of injury documentation and treatment. For more information about my approach to treatment please click HERE.
Chiropractic care for people with injuries
Doctors of chiropractic focus on locating and correcting subluxations using relatively safe, gentle, “adjustment” techniques. Chiropractic care is generally regarded as relatively safe, with serious adverse events reported as rare in recent large-scale research.8
In my clinical experience, people who have been involved in accidents often present with subluxations in multiple areas of the spine and extremities, which appear to be contributing to their ongoing symptoms and physical limitations - even after receiving hospital emergency care.9,10
I studied and worked as a chiropractor for eighteen years in the US. In America, some hospitals have employed chiropractors to assist in these situations. I worked near Fort Carson, Colorado where chiropractors (commissioned military officers) had such long lines of soldiers waiting to see them with a range of injuries and symptoms including chronic neck pain, knee pain, shoulder pain as well as other issues such as low back pain that a few soldiers consulted with me, even though they had to pay for it, rather than wait in those long lines. That experience - seeing the scale of unmet need for injury-focused chiropractic care - was part of what motivated me to continue offering detailed injury assessments at the Body Mind Empowerment Centre in Canberra when I returned from the US.
Military personnel carry a disproportionate burden of musculoskeletal. Image credit: Jason W. Edwards/DVIDS.
Physical problems after injury
Accidents can cause injuries leading to shoulder pain, arm pain, wrist, hand, leg pain, headaches as well as back pain, arthritis pain, and even jaw and facial pain.
I have assisted many injured people with those symptoms. Some people present with one or two conditions and others have had dozens of symptoms develop as a result of a single event such as a car accident. For example, I had one person here in Canberra referred to me by her GP, who had 52 different symptoms after a serious accident. Working systematically through each symptom with her was one of the most clinically satisfying cases I have been involved with.

A chiropractor explaining spinal function to a patient. Image credit: Fatih Ustaosmanoğlu/Pexels.com
One aspect of my approach that patients often find valuable is the time I take at the initial consultation to systematically identify, document and quantify each symptom they are experiencing - not only those they recognise as injury-related, but also those that may have developed gradually over time without an obvious cause. This thorough baseline assessment can be important for several reasons. It may help clarify which symptoms are likely associated with a specific traumatic event, provide a documented starting point against which any changes can be measured over time, and offer a more complete picture of how the injury has affected the person’s daily life and function. For people who are working with a GP or solicitor in relation to an injury claim, this kind of detailed documentation can also serve as a useful clinical record.
For GPs and solicitors: when I see a patient with significant symptoms resulting from injury, I conduct a thorough initial evaluation. Where there is clinical need or a request from the referring clinician, I am happy to discuss my findings and, where appropriate, provide a detailed written report documenting presenting symptoms, clinical findings and any functional changes observed over the course of care. These reports are designed to be useful in the context of injury claims and/or ongoing patient management.
Within the vertebral subluxation model, one clinical objective is to address spinal dysfunction and altered sensory input, with the aim of supporting nervous-system function.7 It is therefore not surprising that chiropractic care is widely used across Australia - according to the Australian Chiropractors Association, over 300,000 Australians visit a chiropractor every week. With NDIS, car accident insurance, DVA, Medicare and workers compensation schemes paying to some extent for chiropractic care, people with access to those programs are seeking assistance after injury.
Research has investigated the use of chiropractic care for some injury-related musculoskeletal conditions. One notable example is a British study titled Chiropractic treatment of chronic ‘whiplash’ injuries, conducted by Woodward, Cook, Gargan and Bannister from the University Department of Orthopaedic Surgery, Bristol - not a chiropractic institution.11 In this study, 28 patients referred with chronic whiplash were assessed before and after treatment, with outcomes evaluated blind by both an independent chiropractor and an orthopaedic surgeon.
In discussing the broader evidence, the authors also referred to prior research comparing chiropractic and conventional care for low back pain; this was contextual discussion rather than an outcome measured in the 28 whiplash patients.
The same study also reported:
““The results of this retrospective study would suggest that benefits can also occur in over ninety percent of patients undergoing chiropractic treatment for chronic ‘whiplash’ injury.””
This was a retrospective study of 28 patients referred for chronic whiplash; it is not a population study, and individual results vary, therefore, results cannot be guaranteed.
Chronic whiplash symptoms can persist long after the original injury, often without a clear visible cause. Image credit: Funkcinės Terapijos Centras/Pexels.com
A follow-up study by the same orthopaedic surgery research group, published in The Journal of Orthopaedic Medicine, found that 69 of 93 participants (74%) showed improvement following treatment. These findings reflect a single study. Both studies should not be taken as a precise prediction of outcomes, but they do indicate that a meaningful proportion of people with chronic whiplash symptoms may experience improvement with chiropractic care. Individual results vary.12
What If Your Chronic Pain Is Due to an Old Injury You Have Almost Forgotten About?
Sometimes the connection between an old injury and today’s pain is not obvious. But the body keeps a long record - and unaddressed joint dysfunction from decades ago may still be influencing how your muscles function and how your joints are coping today. Understanding this connection is one reason why a thorough assessment, sooner rather than later, can matter more than most people realise.
One of the things I look for in every assessment is whether spinal subluxations - the structural spinal distortions we have described earlier in this article - may be contributing to reduced strength in the arms, shoulders or legs. When nerve interference from a subluxation reduces the signal reaching a muscle group, that muscle group may not fire as strongly or coordinate as well as it should. When the muscles around a joint are not coordinating properly, that joint may be exposed to less optimal loading patterns during daily movement. Research has found that people with tibiofemoral knee osteoarthritis were more likely than healthy controls to have lower muscle strength, proprioception deficits and altered joint loading, although the review could not establish causation.21 Research has explored the relationships between spinal dysfunction, sensorimotor integration and motor control. This is one reason I consider strength and movement as part of my clinical assessment following injury. Your doctor may refer to this as degenerative joint disease - also known as DJD - which is a form of arthritis, and it is one of the most common conditions seen in older adults.
Before we go further into the research, it is worth pausing on something that does not always get the attention it deserves - and that is the question of what your nervous system is actually doing when it coordinates movement. To make the most of what follows, it helps to understand one key term first - and I promise it is more fascinating than it might initially sound.
The term sensorimotor integration refers to the process by which your brain and nervous system take in information from your body and surroundings and use that information to control movement. Think of it this way: every time you take a step, reach for a glass, or correct your balance on an uneven surface, your nervous system is gathering signals from muscles, joints, eyes and the inner ear, processing them at remarkable speed, and sending precise instructions back out to your muscles. That continuous loop of sensing and responding is sensorimotor integration. When it works well, movement feels effortless. A systematic review published in Frontiers in Neuroscience reports that impaired multisensory integration may predispose older adults to falls.22 Injury and age-related changes are among the factors that can disrupt sensorimotor function. A peer-reviewed review co-authored by Dr Haavik and colleagues also reports that spinal dysfunction is associated with disordered sensorimotor integration and altered motor control.23 This is one reason why the relationship between spinal function and falls risk has become an active area of chiropractic research.
Research published in the Journal of the American Geriatrics Society has found an association between muscle strength and falls risk in older adults, and the consequences of falls in this group can be serious - including fractures, loss of independence, hospitalisation, and in some cases, death.19
And the research findings here are genuinely encouraging.
The Journal of Manipulative and Physiological Therapeutics - it is worth knowing that this is a prestigious, long-established peer-reviewed journal that originated within the chiropractic profession and remains one of the primary scientific journals where researchers and chiropractors publish their work on spinal health and manual therapy. A systematic review published in this journal examined whether spinal manipulation produces measurable changes in muscle strength and concluded that:
““This review suggests that spinal manipulative therapy augments the percentage of change in isometric strength gain among healthy participants when compared to no intervention or sham manipulation.”16”
In plain language: across the studies included in this review, healthy participants who received spinal manipulation showed greater improvements in objectively measured isometric muscle strength than those receiving no intervention or sham manipulation, although the authors advised that the findings should be interpreted with caution due to differences between the studies. A small study involving 25 people with recurring spinal dysfunction examined the immediate effects of a single spinal manipulation session on maximum voluntary contraction of the ankle dorsiflexor muscles. The researchers found that:
“Compared with the control intervention, maximum voluntary contraction increased significantly after spinal manipulation, averaging 18.87% (SD 28.35%; p = 0.02).17”
This was a statistically significant immediate change in the specific muscle group tested. The study authors noted that longer-term effects and broader functional outcomes are areas requiring further investigation. Maximum voluntary contraction is an objective measure used to assess the maximum force a person can voluntarily produce under the testing conditions - making it a useful and widely used benchmark in strength research.
These findings are particularly interesting to me clinically because assessing and monitoring muscle strength is something I have built into my practice over nearly thirty years. I assess strength from a patient's first visit and continue to monitor it alongside other measures of movement and function throughout care. It is worth being clear that my clinical observations are separate from these particular studies - the research above has important limitations, including small samples and short timeframes - and individual responses vary considerably. What I can say is that I continue to follow the research in this area with genuine interest.
What makes this especially relevant to older patients - and many of my patients are in their 50s, 60s, 70s and beyond - is that the benefits of better spinal function may extend well beyond strength alone. A randomised controlled trial published in the Journal of Manipulative and Physiological Therapeutics - the Holt, Haavik and colleagues study from 2016 - specifically assessed whether twelve weeks of chiropractic care improved sensorimotor function associated with falls risk in community-dwelling adults over the age of 65. Falls risk. In real older people, living in their own homes. The study reported improvements in the chiropractic group compared with the control group in several measures associated with sensorimotor function and falls risk, including choice-stepping reaction time, multisensory integration and ankle joint position sense.18
Falls are not a minor inconvenience for older adults. They are the leading cause of injury-related hospital admissions in people over 65. These findings are interesting because they suggest that chiropractic care may influence some measures of sensorimotor function associated with falls risk in older adults. The researchers noted that further research is needed to determine whether these changes translate into an effect on actual falls risk.
In Australia alone, spending on fall-related injuries was approximately $4.7 billion in 2020–21, according to the Australian Institute of Health and Welfare20 - and that figure does not begin to capture the human cost of pain, lost independence and diminished quality of life that can follow a serious fall.
At a population level, the $4.7 billion cost of fall-related injuries underscores why research into falls prevention across all disciplines - including the emerging body of work on sensorimotor function and chiropractic care - matters for older Australians and the healthcare system that supports them.
Muscle strength and coordination also contribute to joint stability and the control of movement.
The peer-reviewed chiropractic literature supports this connection between spinal function and muscle strength. In the Journal of Electromyography and Kinesiology, Haavik and Murphy wrote that:
““Mild, recurrent spinal dysfunction alters CNS function in ways that impact motor control.”13”
A second body of research takes this further. In a peer-reviewed study published in the European Journal of Applied Physiology, Haavik and colleagues found that:
““The presence of mild, recurrent spinal dysfunction has been shown to be associated with maladaptive neural plastic changes.”14”
The same study noted that these changes include alterations in joint position sense and motor control of the lower limb - functions directly relevant to how well a joint is protected during everyday movement.
Imagine someone who experienced a significant side-impact collision nearly 25 years ago and noticed ongoing leg weakness ever since. Persistent weakness of this kind can indicate reduced muscle coordination around the knee joint, and reduced coordination may mean abnormal forces are going through the joint over time, increasing the likelihood of accelerated wear and degenerative change.
This is not unusual. Research from the Johns Hopkins Precursors Study, published in the Annals of Internal Medicine, followed over 1,300 adults for a median of 36 years - from their mid-twenties through to their early sixties. Those who had suffered a knee injury in young adulthood were found to have nearly three times the risk of developing knee osteoarthritis by age 65, compared to those who had not.15
I’ll repeat that again. That was three times the risk. And that was from an injury that may have felt like a minor inconvenience at the time.
Neck pain and stiffness may develop after
a seemingly minor collision or other traumatic event.
Image credit: Kindel Media/Pexels.com
The mechanism is the same one described earlier in this article. An injury - whether from a car accident, a fall, a sporting collision or simply an awkward movement - can cause subtle changes to how a joint moves. Those changes may produce only mild symptoms at first: a bit of stiffness, occasional aching, muscles that feel tight after activity. Previous joint injury has been associated with an increased risk of degenerative changes over time, although the factors contributing to this are complex and can vary between individuals. By the time the pain becomes significant enough to prompt an X-ray or a GP visit, the degenerative changes may already be well established.
This is why early assessment matters. Not every injury will follow this path - individual results vary, and many people recover fully. But if you have had a significant fall, a bingle, a sporting injury or any trauma to the spine or joints, having that assessed by an experienced clinician sooner rather than later may be one of the most useful things you can do for your future self.
“You’ll have to learn to live with it”
Many people have been told that they’ll just have to “learn to live with it,” but it isn’t always true.
Anyone who has been in an accident or had various forms of trauma, no matter how long ago, may still be able to make progress in their efforts towards recovery with chiropractic care. I have taken care of dozens of people after hospital treatment for injuries ranging from fractured neck, fractured back and two cases of multiple pelvic fractures, to repetitive injury as well as work injuries and car accidents. While I cannot guarantee results, because individual results vary, I have seen cases where chiropractic care has seemed to play a meaningful role in the recovery. This included assisting some people to move from a life of pain, restriction and suffering toward greater ease, productivity and quality of life.
What Nearly 30 Years of Clinical Experience May Mean for You
While it is not possible for any treating provider to predict the level of anticipated success in every case, nearly 30 years of clinical chiropractic experience helps me to assess injured people and have a reasonable level of confidence about whether I can help them to make progress towards a more complete recovery.
Having provided written chiropractic opinions as an official state “Independent Medical Evaluator” in Colorado to dozens of people involved in car accidents who were being treated by other chiropractors, I have seen cases where people received excellent care, as well as cases where that care was less ideal.
This experience leads me to believe that it is important to do a very detailed initial evaluation, and if applicable, to then include treatment, in order to be able to make a prediction about whether or not the person is likely to make progress.
If, after my detailed initial evaluation, I find good evidence that progress is likely, then I will recommend a specific treatment plan with a thorough re-evaluation in 4 to 8 weeks. At that point, I will usually provide a detailed written report documenting my findings to your GP. I may then be able to include documented findings on any symptomatic and functional changes observed over the course of care.
Several GPs and solicitors in Canberra have found that this approach has been helpful in better understanding the nature of injuries for some of their patients and clients. Another goal of mine is to document the negative impact that injuries may have had upon the lives of my injured patients; then, to document any progress in patient mobility and quality of life using objective questionnaires during their re-evaluations.

Good communication between practitioners can support a coordinated approach especially when different forms of care may complement one another.
Image credit: Antoni Shkraba/Pexels.com
I have benefited from physio myself and all my children have sought assistance from physiotherapists. I have had some injury cases where I have had the opportunity to interact with the patient’s physiotherapist to the benefit of the patient. My objectives and methods can be different from those of the physiotherapist and given a physio’s work can be very beneficial, with good communication, there are times where both chiropractic and physio together, may offer more to the patient than just one or the other.
If you have had an accident or injury and would like to find out whether chiropractic care may be appropriate for you, I welcome an initial conversation. You can reach the Body Mind Empowerment Centre on (02) 6162 2919 or at vitality@bodymindec.com.au. You can also check the services page for the low-cost initial consultation option.
My wish for you is to move better, feel better, and live better,
Jason W. Barritt B.Sc (Hons) DC
Please note: the findings discussed in the above article reflect research associations, not guaranteed outcomes. Individual results vary. This content is for general health education purposes only. For specific health concerns, please consult with a registered healthcare professional in person.
References
1. Poorbaugh K, Brismée J-M, Phelps V, Sizer PS Jr. Late whiplash syndrome: a clinical science approach to evidence-based diagnosis and management. Pain Pract. 2008;8(1):65-87. doi:10.1111/j.1533-2500.2007.00168.x.
2. Hamer AJ, Gargan MF, Bannister GC, Nelson RJ. Whiplash injury and surgically treated cervical disc disease. Injury. 1993;24(8):549-550. doi:10.1016/0020-1383(93)90035-5.
3. Yong-Hing K, Kirkaldy-Willis WH. The pathophysiology of degenerative disease of the lumbar spine. Orthop Clin North Am. 1983;14(3):491-504. PMID:6346204.
4. Millan M, Leboeuf-Yde C, Budgell B, Descarreaux M, Amorim M-A. The effect of spinal manipulative therapy on spinal range of motion: a systematic literature review. Chiropr Man Therap. 2012;20(1):23. doi:10.1186/2045-709X-20-23.
5. Williams B. The exploration of potential spinal manipulation effects. J Contemp Chiropr. 2024;7(1):32-50.
6. Fagundes Loss J, de Souza da Silva L, Ferreira Miranda I, Groisman S, Santiago Wagner Neto E, Souza C, et al. Immediate effects of a lumbar spine manipulation on pain sensitivity and postural control in individuals with nonspecific low back pain: a randomized controlled trial. Chiropr Man Therap. 2020;28:25. doi:10.1186/s12998-020-00316-7.
7. Haavik Taylor H, Holt K, Murphy B. Exploring the neuromodulatory effects of the vertebral subluxation and chiropractic care. Chiropr J Aust. 2010;40(1):37-44.
8. Chu ECP, Trager RJ, Lee LYK, Niazi IK. A retrospective analysis of the incidence of severe adverse events among recipients of chiropractic spinal manipulative therapy. Sci Rep. 2023;13(1):1254. doi:10.1038/s41598-023-28520-4. PMCID:PMC9870863.
9. Tanaka N. Pathology and treatment of traumatic cervical spine syndrome: whiplash injury. Adv Orthop. 2018;2018:4765050. doi:10.1155/2018/4765050. PMCID:PMC5851023.
10. Kasch H, Carstensen T, Ravn SL, Andersen TE, Frostholm L. Cervical motor and nociceptive dysfunction after an acute whiplash injury and the association with long-term non-recovery: revisiting a one-year prospective cohort with ankle injured controls. Front Pain Res (Lausanne). 2022;3:906638. doi:10.3389/fpain.2022.906638. PMCID:PMC9300940.
11. Woodward MN, Cook JCH, Gargan MF, Bannister GC. Chiropractic treatment of chronic ‘whiplash’ injuries. Injury. 1996;27(9):643-645. doi:10.1016/S0020-1383(96)00096-4.
12. Khan S, Cook JCH, Gargan MF, Bannister GC. A symptomatic classification of whiplash injury and the implications for treatment. J Orthop Med. 1999;21(1):22-25. doi:10.1080/1355297X.1999.11719898.
13. Haavik H, Murphy B. The role of spinal manipulation in addressing disordered sensorimotor integration and altered motor control. J Electromyogr Kinesiol. 2012;22(5):768-776. doi:10.1016/j.jelekin.2012.02.012.
14. Christiansen TL, Niazi IK, Holt K, Nedergaard RW, Duehr J, Allen K, Marshall P, Türker KS, Hartvigsen J, Haavik H. The effects of a single session of spinal manipulation on strength and cortical drive in athletes. Eur J Appl Physiol. 2018;118(4):737-749. doi:10.1007/s00421-018-3799-x.
15. Gelber AC, Hochberg MC, Mead LA, Wang N-Y, Wigley FM, Klag MJ. Joint injury in young adults and risk for subsequent knee and hip osteoarthritis. Ann Intern Med. 2000;133(5):321-328. doi:10.7326/0003-4819-133-5-200009050-00007.
16. Lo CN, Ng J, Au CK, Lim ECW. The effectiveness of spinal manipulation in increasing muscle strength in healthy individuals: a systematic review and meta-analysis. J Manipulative Physiol Ther. 2019;42(2):148-158. doi:10.1016/j.jmpt.2018.10.003. PMID:31126523.
17. Niazi IK, Kamavuako EN, Holt K, Janjua TAM, Kumari N, Amjad I, Haavik H. The effect of spinal manipulation on the electrophysiological and metabolic properties of the tibialis anterior muscle. Healthcare (Basel). 2020;8(4):548. doi:10.3390/healthcare8040548. PMCID:PMC7764559.
18. Holt K, Haavik H, Lee AC, Murphy B, Elley CR. Effectiveness of chiropractic care to improve sensorimotor function associated with falls risk in older people: a randomized controlled trial. J Manipulative Physiol Ther. 2016;39(4):267-278. doi:10.1016/j.jmpt.2016.02.003.
19. Moreland JD, Richardson JA, Goldsmith CH, Clase CM. Muscle weakness and falls in older adults: a systematic review and meta-analysis. J Am Geriatr Soc. 2004;52(7):1121-1129. doi:10.1111/j.1532-5415.2004.52310.x.
20. Australian Institute of Health and Welfare. Health system spending on disease and injury in Australia, 2020–21 [Internet]. Canberra: AIHW; 2023 [cited 2026 Sep 7]. Available from: https://www.aihw.gov.au/reports/health-welfare-expenditure/health-system-spending-on-disease-and-injury-in-au
21. van Tunen JAC, Dell'Isola A, Juhl C, Dekker J, Steultjens M, Thorlund JB, Lund H. Association of malalignment, muscular dysfunction, proprioception, laxity and abnormal joint loading with tibiofemoral knee osteoarthritis: a systematic review and meta-analysis. BMC Musculoskelet Disord. 2018;19(1):273. doi:10.1186/s12891-018-2202-8. PMCID:PMC6064629.
22. Zhang S, Xu W, Zhu Y, Tian E, Kong W. Impaired multisensory integration predisposes the elderly people to fall: a systematic review. Front Neurosci. 2020;14:411. doi:10.3389/fnins.2020.00411. PMCID:PMC7198912.
23. Haavik H, Kumari N, Holt K, Niazi IK, Amjad I, Pujari AN, Türker KS, Murphy B. The contemporary model of vertebral column joint dysfunction and impact of high-velocity, low-amplitude controlled vertebral thrusts on neuromuscular function. Eur J Appl Physiol. 2021;121(10):2675-2720. doi:10.1007/s00421-021-04727-z. PMCID:PMC8416873.
Supporting Research Notes
The following notes provide additional context for readers who wish to explore some of the research cited throughout this article in greater depth. They are not essential to understanding the article but are included for those interested in the supporting literature.
7. Vertebral subluxation and nerve interference
This peer-reviewed paper reviews neurologic research underpinning a proposed model in which altered afferent input from the spine may contribute to maladaptive neural changes. For a fuller conceptual definition, see also: Australian Spinal Research Foundation. The Vertebral Subluxation: Conceptual Definition for Research and Practice. 2017. https://spinalresearch.com.au/wp-content/uploads/2017/06/The-Vertebral-Subluxation.pdf. This is an organisational consultation document, not a peer-reviewed journal article; the Foundation reports a nine-month consultation involving 59 chiropractic leaders, researchers and academics across nine countries.
8. Safety of chiropractic care
This retrospective dataset of 960,140 treatments found two grade-3 adverse events and no grade-4 or grade-5 events; the authors described severe events as very rare in this dataset. This study (Chu et al., 2023) is also listed as Reference 8 above. For additional context, an earlier systematic review found that most reported adverse events were benign and transient while also identifying reports of serious complications; it did not establish a precise population incidence: Gouveia LO, Castanho P, Ferreira JJ. Safety of chiropractic interventions: a systematic review. Spine (Phila Pa 1976). 2009;34(11):E405-E413. doi:10.1097/BRS.0b013e3181a16d63.
9, 10. Persistence of post-traumatic spinal dysfunction following whiplash injury
Persistent symptoms following whiplash-type trauma - including neck pain, headaches, dizziness and extremity numbness - have been reported to continue for more than six months in approximately one third of patients, as reported by Tanaka (2018).
Two terms in the Kasch et al. study below are worth briefly explaining. Cervical motor dysfunction refers to impaired control of the muscles that move and stabilise the neck - essentially, the neck is not moving or being controlled in the way it should be. Segmental nociceptive sensitisation refers to a process whereby a specific segment or level of the spine becomes abnormally sensitive to pain signals, so that sensations that would normally be mild or neutral are experienced as painful. When these two processes occur together and persist after injury, they indicate that the nervous system itself has been affected, not just the muscles and joints.
A one-year prospective cohort study by Kasch et al. (2022) found that both of these processes - impaired neck motor control and heightened spinal pain sensitivity - were measurable from early after whiplash injury and remained prolonged in patients who did not recover. This indicates that such dysfunction can persist well beyond the acute emergency phase, representing an ongoing neurological and musculoskeletal challenge rather than a simple soft tissue injury.
Further Reading
The following historical publications informed the broader background and development of ideas discussed in this article but are not directly cited in the body text. They are included for readers interested in exploring the historical literature relating to spinal trauma and post-traumatic cervical syndromes.
• Hadley LA. Intervertebral joint subluxation, bony impingement and foramen encroachment with nerve root changes. Am J Roentgenol Radium Ther. 1951;65(3):377-402.
• Braaf MM, Rosner S. Trauma of cervical spine as cause of chronic headache. J Trauma. 1975;15(5):441-446. doi:10.1097/00005373-197505000-00011.
• Gukelberger M. The uncomplicated post-traumatic cervical syndrome. Scand J Rehabil Med. 1972;4:150-153.